Commission and Incentives for Diagnostic centres
Calculate incentive amounts from approved sales or collection rules.
Does this function belong in your operation?
Use when compensation depends on recorded sales, collections or other agreed outcomes.
A commission period is ready for review.
Referring doctors and collection agents are paid by agreed rates on scans and tests billed. Reversals follow cancelled studies. The accounts team reads the payout from signed bills.
Bring the records the workflow depends on.
- Eligible transactions
- Commission rules and dates
- Participant assignments
Outputs to check
- Transaction-level incentive calculation
- Adjustment and approval statement
- Payout handoff record
Follow the commission and incentives workflow.
Use this sequence to compare your current process with the proposed module. Agree the owner, permission and exception at each step.
Who uses the module, and who approves?
Keep responsibilities distinct even when one person holds more than one role.
Decide how exceptions are handled.
These business rules belong in configuration and testing. A normal transaction alone does not demonstrate that the workflow is ready.
Can this work independently?
Calculation needs eligible sales or collection records and effective-dated rules. It can run from imports without payroll, but payroll or accounts performs the payment. Returns, credits and reversals must feed the calculation so a booked sale is not rewarded twice or retained after reversal.
Systems and records it connects with
- Invoice management: Issued invoice references, line amounts and outstanding balances.
- Receipts management: Recorded customer payments and invoice allocations.
- Collections and follow-up: Due balances, payment promises and follow-up outcomes.
- Payroll: Approved pay inputs, deduction calculations and payment instructions.
Configure, test and introduce the workflow.
- You describe how each role is paid, on paper or aloud. You get a written note of each rule in plain language to confirm. Plain words are enough.
- Old and new rates are entered with the dates they apply from. You get a screen to check a past month against what was paid. Past months are good tests. Statements are produced for a few people from last month’s bills. They read them, and you hear what does not match. People check their own.
- You decide what pulls a commission back and when. The rules are tested with returned orders and bounced cheques. Edge cases come out here. The accounts team prepares payouts from the statements and marks them. Staff are shown how to read their own statement. Questions drop quickly.
Check the result before rollout.
Apply these checks to a sample from the agreed workflow, then repeat with an exception. Keep the expected result beside the test record.
- Calculations trace to qualifying transactions.
- Returns follow the agreed reversal rule.
- Rule changes use the correct effective date.
How the business operates.
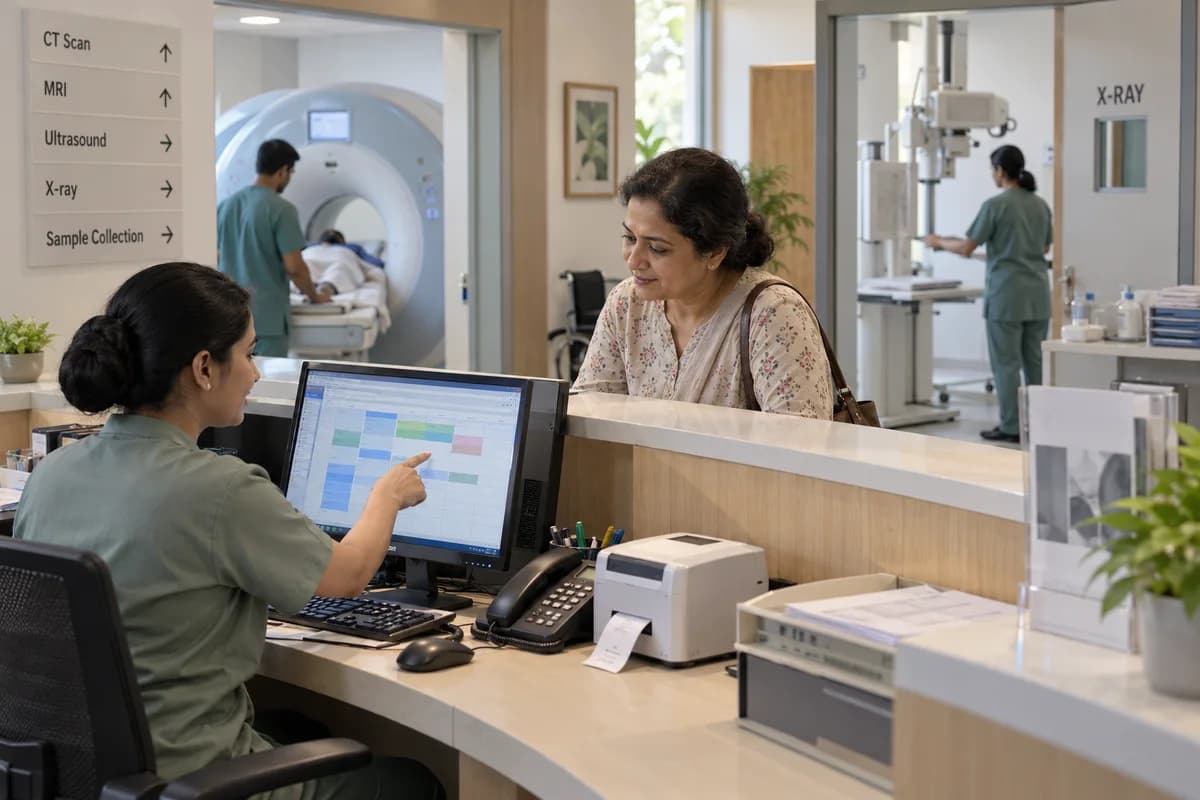
A centre with an X-ray room, two ultrasound rooms and a CT scanner handles walk-ins, booked scans, hospital referrals and health check packages through one front desk. That desk is the bottleneck.
The records that hold the operation together.
- Patient registration and visits. Register each patient once, found by phone number or ID, with every visit, prescription, referrer and report on the same record.
- Slot booking by machine. Book ultrasound, X-ray, CT, MRI and other rooms by slot. The preparation each scan needs is printed or sent at booking, so fasting and test values are asked for in advance.
- Rate lists and health packages. Keep separate rate lists for walk-ins, hospitals, corporates and camps. Group scans and tests into health check packages.
- Billing, dues and refunds. Bill each visit from the right rate list, take part payments, record every discount with the person who approved it, and refund a cancelled scan with the reason written down.
Operational bottlenecks to check
Every machine keeps its own diary
Ultrasound uses a register, CT uses a sheet, and the desk cannot see either while a caller waits on the line. Double bookings follow.
Preparation is missed
A patient arrives for an abdomen scan after breakfast, or for a contrast study without a recent creatinine value. The slot is lost.
How work flows across this business
This module sits within a wider operating process. Use the sequence to identify the other teams and records affected by a change.
1. Booking
A patient or a referring doctor books by phone, on WhatsApp or at the desk. The slot goes on a machine and room, and the preparation instructions go with it.
2. Registration and billing
The desk registers the patient, notes the referrer and the prescription, and bills from the rate list that applies. Cash, bank transfer, card or a credit account settles the visit.
3. Scan
The technician sees the room’s worklist, checks preparation and consent, and marks the study scanned. Images go to the centre’s PACS or viewer.
4. Reporting
The radiologist opens the study, writes findings from a template and signs. A critical finding is flagged so the referring doctor gets a call.
5. Delivery
Signed reports are printed with films or a CD, or sent as a PDF. Messages go through the centre’s own WhatsApp Business account where that is set up.
6. Month end
Credit visits roll into statements for each hospital and corporate. The owner sees studies by machine, modality and referrer.
Industry reports to connect with
- Studies by modality, machine and day
- Reports awaiting sign-off, by radiologist
- Visits by referring doctor and hospital
- Credit dues by hospital and corporate
Questions before implementation.
When should diagnostic centres consider commission and incentives?
Use when compensation depends on recorded sales, collections or other agreed outcomes. A commission period is ready for review.
What should we bring to the requirements discussion?
Bring anonymised examples of Eligible transactions; Commission rules and dates; Participant assignments. Show who creates, checks and changes each record. Use only records from an activity that meets the suitability conditions above.
Does this replace our existing business software?
The starting point is your current system and the gap you need to close. Calculate incentive amounts from approved sales or collection rules. Configuration, a connected module or a custom build are evaluated against that gap before a replacement is proposed.
What is outside this module?
Employment terms, tax treatment and payout approval remain with your authorised team.
How are scope, price and rollout decided?
The proposal follows a review of your records, user roles, branches and existing software. Data migration, connections, training and support are scoped separately where needed. Calculations trace to qualifying transactions. Use this check when reviewing the first working version.
Related functions for diagnostic centres.
Discuss commission and incentives for your business.
Tell us which workflow needs attention and which systems your team uses. The next step is a requirements discussion and a written scope.
What happens after you share your requirements
- We review your brief and the systems you already use.
- We clarify the workflow, missing information and the work to consider first.
- The proposed scope sets out the deliverables, responsibilities and dependencies.
- Review the scope and commercial terms before deciding whether to proceed.
Start with your requirements
Describe your current process, the people involved and the change you need. Start with the details you know; we can clarify the rest together.
Share your requirements